
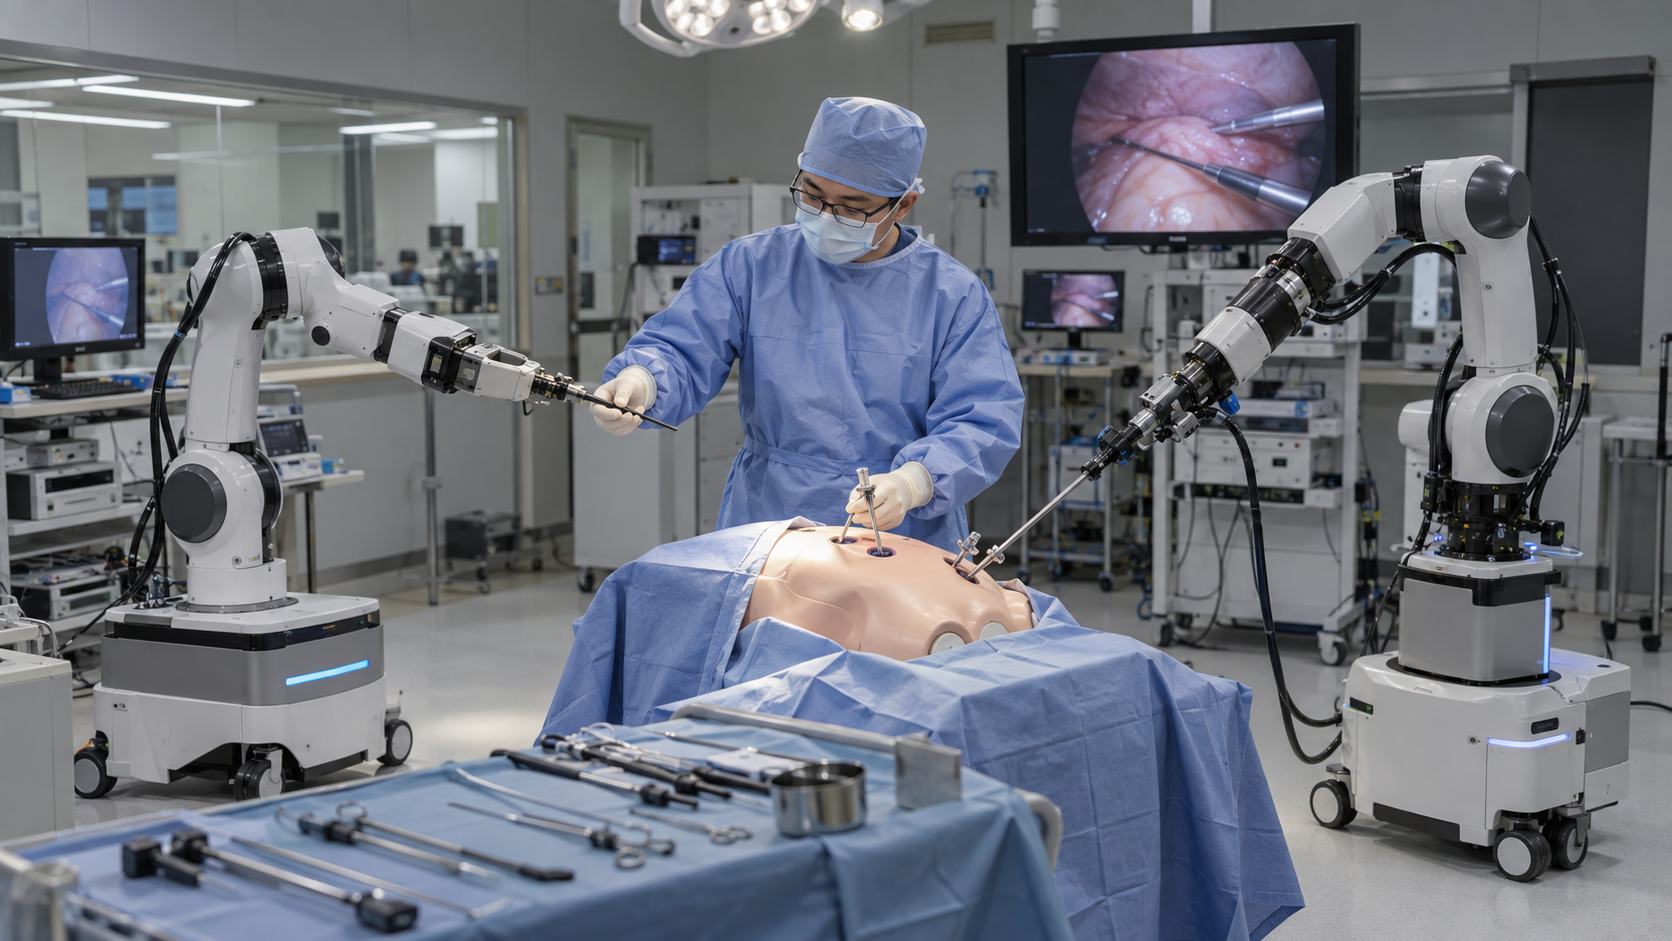
Two humanoid robots have assisted a surgeon in a simulated gallbladder operation in Seoul. One identified and passed surgical instruments after spoken requests; the other held the laparoscope, adjusted the camera view and pulled tissue to keep the operating field accessible. The demonstration makes a previously abstract idea visible: a humanoid may become an assistant around the operating table rather than the machine through which the surgeon performs the operation.
The event took place on September 16 in a surgical simulation environment operated by Samsung Medical Center. The procedure used a goat liver, not a human patient, and the project has not entered clinical trials. That distinction is essential. The ORchestra research consortium has demonstrated several narrowly defined assistance functions under controlled conditions. It has not shown that humanoid robots can independently perform surgery or improve outcomes for patients.
ORchestra stands for Operating Room Collaborative Humanoid. Samsung Medical Center leads the five-year Korean ARPA-H project with hospitals, universities and robotics companies. Rainbow Robotics develops the body, while AIDIN Robotics supplies the gripper and hand. The National Cancer Center, Jeonbuk National University Hospital, Seoul National University and Sungkyunkwan University also participate.
In this article
What the robots actually did
The demonstration combined two forms of assistance. In one sequence, robots were teleoperated. In the more distinctive scenario, a human surgeon worked with two robotic assistants beside the operating table. The surgeon retained authority and issued spoken instructions.
The first robot performed a circulating-nurse-style task. A camera viewed an instrument tray, software distinguished tools such as scissors, clips and graspers, and the robot selected the requested object. It then oriented the handle toward the surgeon for a handover and later accepted the used instrument back. The tool was not simply collected from one permanently programmed coordinate; the system used visual information to identify its type and position.
The second robot acted more like an assistant surgeon. It held the laparoscope and adjusted the view in response to commands and observed movement. It also used forceps to retract tissue, creating space for the surgeon. Reports from the demonstration describe visual servoing: camera feedback continuously influences the robot’s movement so that the relevant region remains in view.
These jobs are less spectacular than autonomous cutting, but they are operationally meaningful. Holding an endoscope steadily through a long procedure is physically tiring. Passing instruments requires attention, correct orientation and predictable timing. Reducing that workload could help teams where staffing is limited and offers a more realistic early target than asking a machine to make clinical decisions.
The reported success rates need context
The team reported a 100 percent grasping success rate across five types of surgical instruments and a 98.7 percent handover success rate in laboratory evaluation. Those figures are promising, but the available reports do not provide enough methodological detail for a clinical conclusion. The number of trials, the range of tool positions, lighting variations, occlusions and the handling of failed attempts are not fully described in the public material.
A controlled instrument tray is also very different from a crowded operating room. Tools may overlap, reflect strong light or become partly hidden by hands and drapes. Staff move unpredictably, spoken commands compete with alarms and conversation, and every object entering the sterile field must be managed through strict procedures. A robot that succeeds hundreds of times in a laboratory may still require a carefully designed fallback when the next handover fails.
The results therefore support a limited statement: the consortium has built a functioning prototype for specific perception-and-handover tasks. They do not establish reliability across hospitals, surgeons or procedures. No patient outcome or complication rate has yet been measured in clinical use.
Why this is not an autonomous surgical robot
The word “surgery” can make the demonstration sound more autonomous than it was. The robots did not decide what operation to perform, diagnose a condition or determine where to cut. A human surgeon controlled the procedure. Some movements were directly teleoperated, while other assistance functions responded to voice commands and visual feedback.
That is also what separates ORchestra from the most familiar surgical-robot model. Systems such as da Vinci are console-operated instruments: the surgeon sits at a workstation and directly controls robotic manipulators. ORchestra explores robots that share the physical workspace around the table and take on selected assistant roles. The technical challenge shifts from translating a surgeon’s hand motion to understanding requests, recognising objects, coordinating with people and remaining safe when the situation changes.
The distinction matters for regulation and responsibility. A voice recognition error should never lead directly to an unsafe movement. The system needs confirmation logic, movement limits, collision avoidance and an immediate way for staff to stop or override it. The safest architecture may keep artificial intelligence in perception and task selection while independent, deterministic controls enforce physical boundaries.
The difficult work begins after the demonstration
Moving from a prototype to a clinical device will require more than higher grasping accuracy. Hardware must tolerate repeated cleaning and sterilisation workflows without degrading cameras, seals, cables or force sensors. Robotic arms need safe trajectories around clinicians, anaesthesia equipment, monitors and the patient. The system must recognise when it is uncertain instead of confidently choosing the wrong instrument.
Human factors are equally important. A handover that takes five seconds may be acceptable in one part of a procedure and disruptive in another. Surgeons and nurses need clear signals showing what the robot understood and what it will do next. Spoken commands must work across accents, masks and background noise. Training cannot assume that every hospital uses the same instrument layout or communication style.
Reliability also has to be measured as a workflow, not as isolated skills. A robot may identify a tool correctly but approach from an awkward direction, block another staff member or fail to return the instrument to the expected place. A useful trial should record interventions, delays, near-collisions, misunderstood commands and recovery time alongside successful grasps.
The consortium is roughly 15 months into a five-year programme and has mentioned 2029 as a target for an initial clinical trial. That timetable signals the current maturity more accurately than the dramatic images. The project is advancing from laboratory components toward an integrated operating-room assistant, but clinical validation remains ahead.
What could change if the concept works
The strongest case is not replacing surgeons. It is redistributing repetitive assistance tasks under human control. In hospitals facing shortages, a reliable robot could hold an endoscope, maintain a view or manage instruments while qualified staff concentrate on decisions that require clinical judgment. It could also make movements more consistent during long procedures and document when assistance was requested and completed.
That benefit will depend on economics and integration. Hospitals would need to compare the cost of the robot, maintenance, sterile accessories, training and technical support with the staffing burden it actually reduces. A machine used for only a small number of procedures may be difficult to justify. A platform that can support several surgical specialties without lengthy reconfiguration would have a stronger case, but that versatility has not yet been demonstrated.
Alpha Bionic’s conclusion is therefore deliberately narrower than the headline images. ORchestra has produced a credible proof of concept for humanoid assistance around an operating table. Its instrument recognition, handover and camera-control functions address real work rather than a theatrical movement demo. The decisive evidence will come later: repeated operation in realistic sterile workflows, transparent failure data and supervised clinical trials. Until then, this is an important research milestone—not an autonomous robotic surgeon.
Sources
- Health Chosun: “Please hand me the grasper”—AI robot enters the operating room, September 17, 2026
- Aju Press: Samsung Hospital unveils humanoid surgical assistant robot, September 17, 2026
- ETNews: surgeon and humanoid robots demonstrate collaborative operation, September 17, 2026
- Rainbow Robotics: report on the ORchestra demonstration, September 17, 2026